

Body-composition peptides are short signaling molecules studied for lean-mass support, adipocyte signaling, and growth-hormone axis modulation in metabolic research.
Body Composition
All products listed under this goal are supplied for in vitro laboratory research only and are not intended for human consumption or therapeutic use.
Peptides that support lean, measured progress — not crash results.
Peptides chosen for measured, sustainable progress — each with visible testing, clear dosage, and no crash promises.
- How is body composition different from general metabolic support?
- Which peptides are most often paired with training?
- Where can I see the lab results for each batch?
A short list of peptides that fit this goal.
We keep the choice focused. Every peptide here has a clear purpose, ISO/IEC 17025 lab testing, and a product page written without jargon.

A triple agonist peptide targeting GIP, GLP-1, and glucagon receptors — studied in advanced metabolic and weight-regulation contexts.
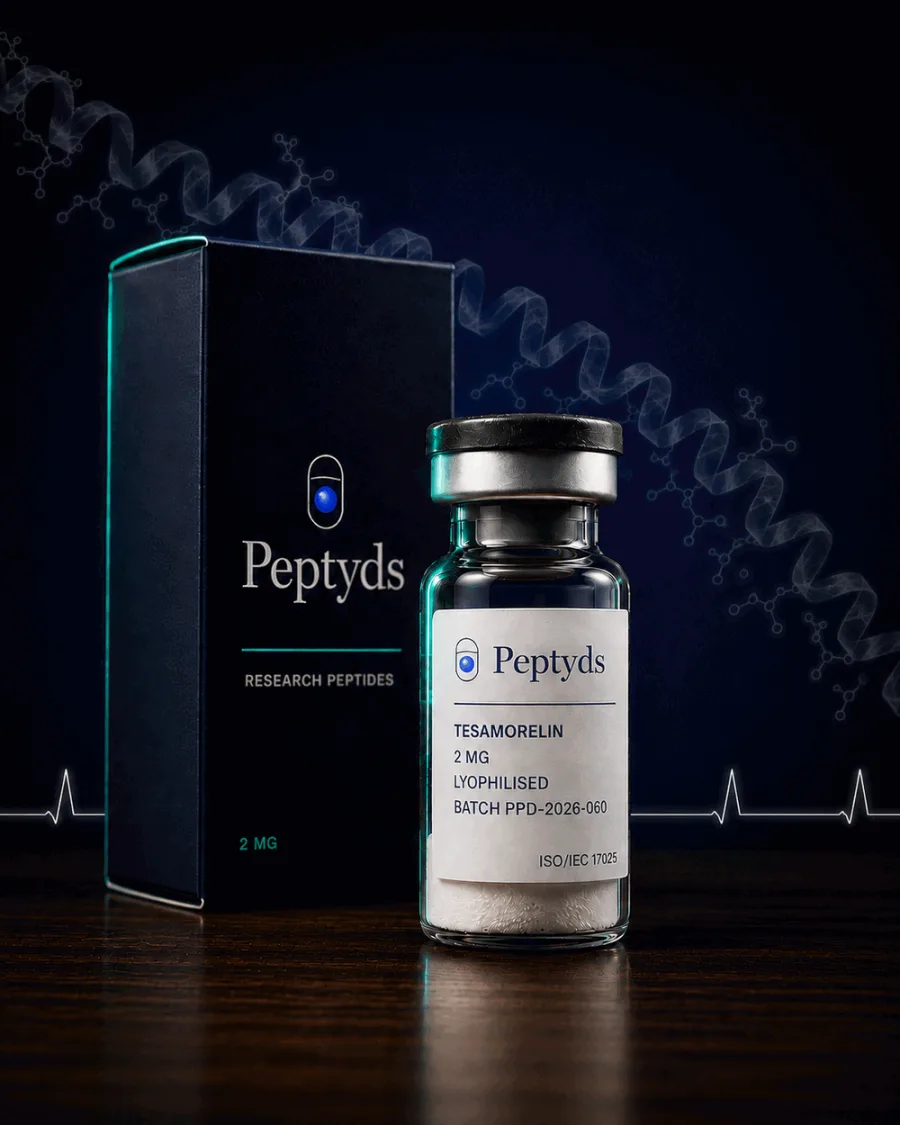
A GHRH analogue studied for visceral fat reduction and body-composition support — used in clinician-supervised metabolic and growth hormone contexts.
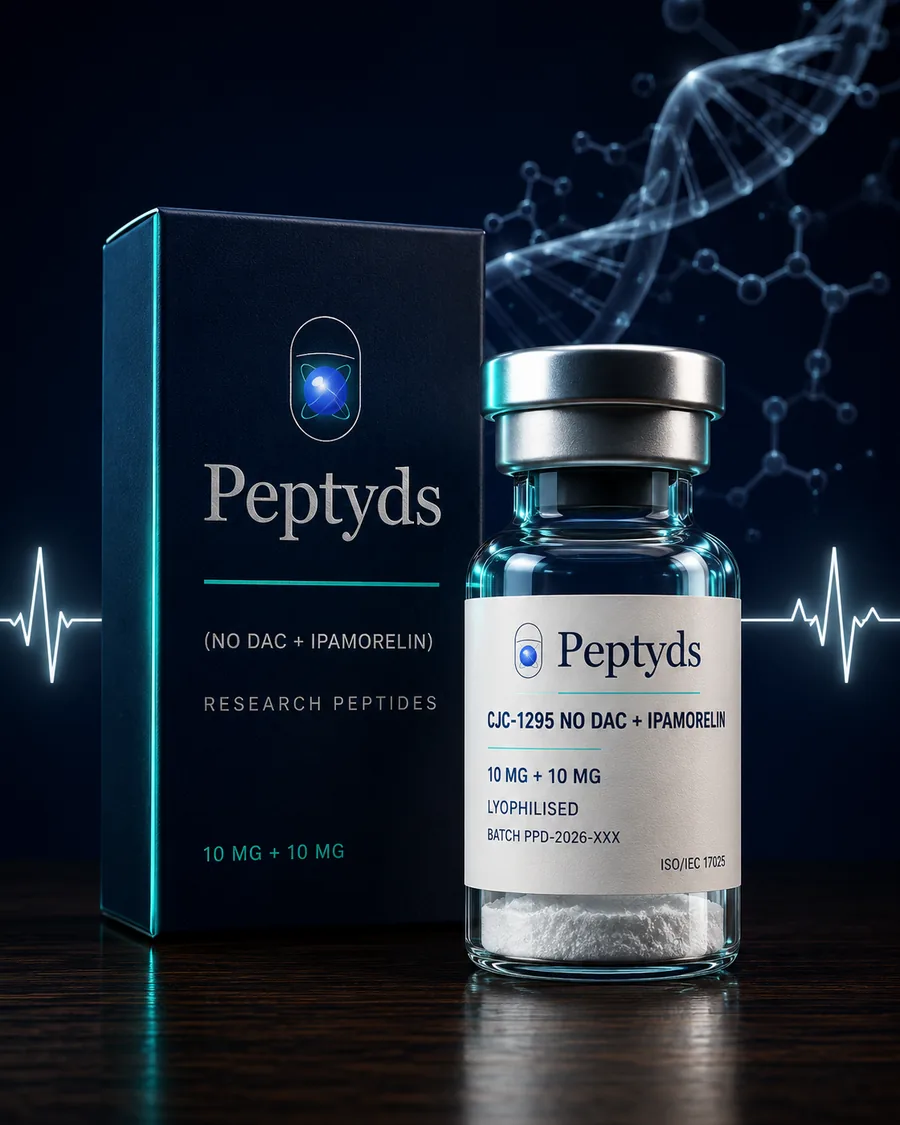
A dual-pathway GH secretagogue blend studied for synergistic, pulsatile growth hormone release — investigated in overnight recovery, sleep architecture, and body-composition research.

A GHRH analogue studied for endogenous growth hormone stimulation — investigated in body-composition, sleep, and healthy-aging contexts.

Ibutamoren mesylate — an orally active ghrelin receptor agonist studied for GH pulse amplification, lean muscle accretion, and sleep-architecture support.
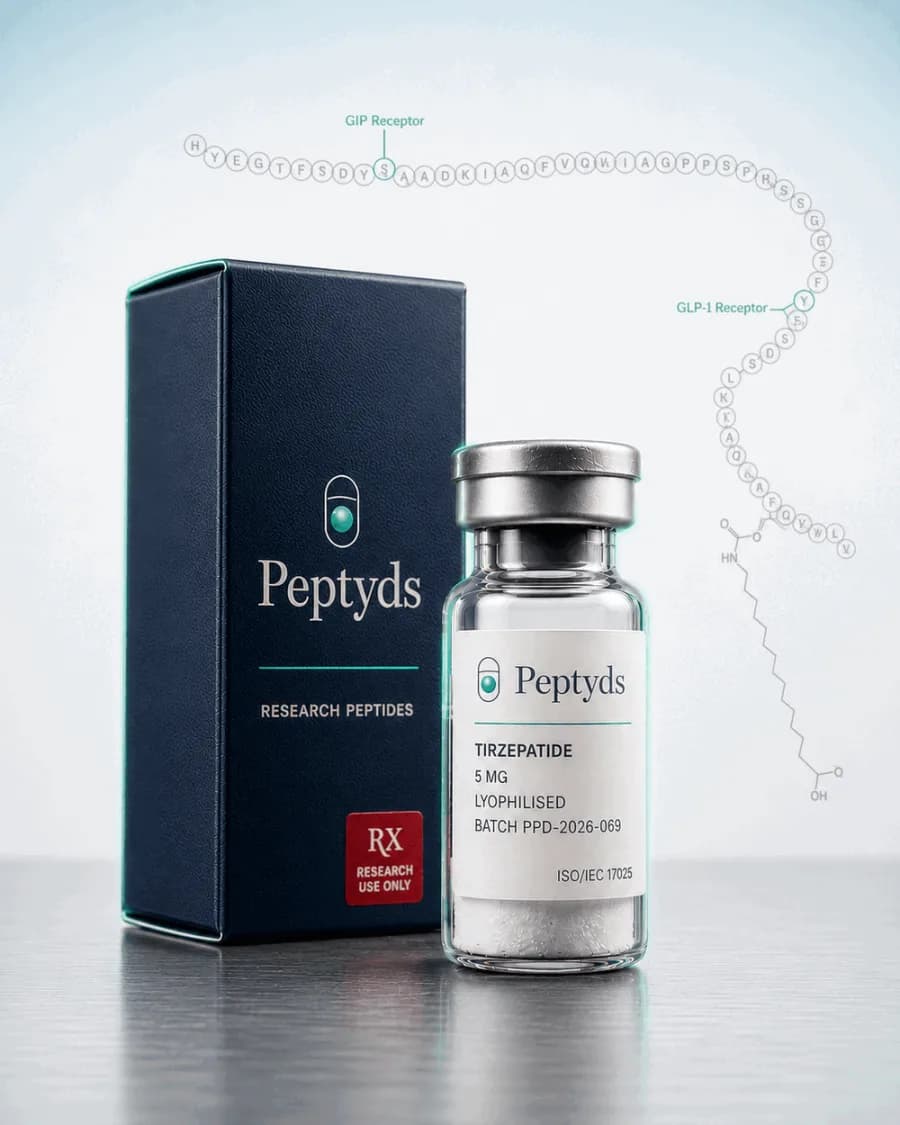
A dual GIP/GLP-1 receptor agonist studied for its effects on appetite regulation, metabolic balance, and body composition — framed for clinician-guided routines.

A long-acting IGF-1 analogue studied for anabolic signalling and measured body-composition support — framed for clinician-guided recovery protocols.
- goal-differentiation
- product-comparison
Each release is matched with quality documentation through a documented verification path. Identity, purity, and composition test results sit on the product page before you buy.
Every batch is verified by an ISO/IEC 17025-accredited laboratory before release. Identity, purity, and documentation travel with the product — not behind a form.
GLP-1 is no longer one simple bucket. Semaglutide, tirzepatide, and retatrutide sit in different evidence and mechanism contexts.
The two are usually compared on one number — how much weight came off. That number favours retatrutide, and it is also the least useful basis for choosing between them.
This pairing sets the widest gap in the GLP-1 family: one receptor against three, and a decade of authorised use against a single published phase 2 trial.
This is the question underneath the entire growth-hormone category, and most comparisons skip it: are you adding the hormone, or asking the body for more of its own?
CJC-1295 and ipamorelin are talked about together because they hit two different parts of the growth-hormone axis. The interesting part of the comparison is mechanism, not which one is 'stronger'.
MK-677 (ibutamoren) is a non-peptide small-molecule oral ghrelin-receptor agonist. Most marketing calls it a peptide. This guide corrects the category and walks through the actual research.
Sermorelin, CJC-1295 and tesamorelin are three different points on the same GHRH map. None is EMA-authorised; only tesamorelin is an approved medicine (FDA, HIV-associated lipodystrophy) — and that matters more than any forum stack ever will.
Both molecules hit the same ghrelin receptor. One is an injectable pentapeptide, the other is an oral small molecule. The mechanism overlaps; almost everything else doesn't.
Tesamorelin is the rare GHRH analogue with a randomised-controlled-trial dataset behind it — but only in one specific clinical population. The honest version separates that data from the consumer marketing.
Three molecules that all touch the GH/IGF-1 axis, three completely different mechanisms, three very different evidence bases. The honest comparison is structural, not which-is-best.
'CJC-1295' names two different molecules, and the popular blend pairs the less-studied one with ipamorelin. This is what the research covers, and what it does not.
IGF-1 is one of the body's central growth signals. IGF-1 LR3 is a laboratory analogue built to slip past its binding proteins, and the 'long-acting' reputation it carries is the opposite of what was measured.
Ipamorelin earned its 'selective' reputation in pigs, its human record stops at pharmacokinetics and one negative phase 2 trial, and its best-known claims were never tested. This is the full record.
Almost every 'muscle peptide' works through the growth-hormone axis. Human trials show modest lean-mass gains in specific groups and no strength gains — and several best-sellers have never been studied in people.
Retatrutide is the most-discussed investigational weight-loss peptide online. The published record is narrower than the hype: strong phase 2 data, a first phase 3 trial in diabetes, and open questions on long-term safety.
Sermorelin is the shortest fully active piece of GHRH and the only member of its family that was once an approved medicine. What the Geref-era data show, and what 'does sermorelin work?' honestly depends on.
Retatrutide is not an approved retail medicine, so a vial's label is not proof of what is inside. Here is how mass spectrometry confirms identity, how HPLC estimates purity, and what published testing of grey-market GLP-1 products has actually found.
Tesamorelin and ipamorelin both end at the same pituitary GH pulse, but they start from different receptors and carry very different evidence: one has a positive HIV-lipodystrophy trial behind an FDA approval, the other has a negative ileus trial and a selectivity claim that is still animal-only.
Nine GLP-1-pathway obesity molecules beyond semaglutide and tirzepatide, grouped by mechanism, each with its most advanced published trial result and regulatory status as of September 2026.
Survodutide is Boehringer Ingelheim's glucagon/GLP-1 dual agonist, tested in obesity and in MASH under the SYNCHRONIZE and LIVERAGE trial programmes. This is what the published phase 2 and phase 3 evidence shows, and where it stood as of September 2026.
CJC-1295 with DAC is the original, multi-day version of the molecule — the one behind the published human growth-hormone trials. Peptyds does not sell it; here is what the research and its history actually show.
Questions people ask about this category.
Honest, short answers to the things most shoppers want to know before they buy.
Several research peptides we list — including BPC-157, TB-500, GHRPs, and IGF-1 LR3 — are listed on the WADA Prohibited List under classes S0 (unapproved substances) and S2 (peptide hormones and growth factors). They are prohibited at all times, in and out of competition.
Semaglutide is a single GLP-1 receptor agonist; tirzepatide is a dual GLP-1 and GIP receptor agonist, which is associated with larger weight reductions in head-to-head trials — roughly 20–22 percent versus 15 percent over 72 weeks in SURMOUNT-5. Both are EMA-approved as prescription medicines (Wegovy/Ozempic and Mounjaro).
Across SUSTAIN, SURPASS, SURMOUNT, and TRIUMPH trials, the dominant adverse events for semaglutide, tirzepatide, and retatrutide are gastrointestinal: nausea, vomiting, diarrhoea, constipation, and abdominal discomfort, usually mild-to-moderate and concentrated during dose titration.
Bring both the lyophilised vial and the bacteriostatic water to room temperature, equalise pressure with a sterile vented needle, then inject the solvent slowly down the side of the vial. Swirl gently — never shake — until clear, and refrigerate at 2–8 °C.
The calculation is peptide mass (mg) ÷ desired concentration (mg/mL) = volume of bacteriostatic water in mL. For example, a 5 mg vial at 1 mg/mL needs 5 mL; at 2 mg/mL, 2.5 mL. Every Peptyds product page carries a suggested reconstitution volume tuned to the vial size.